What's Happening?
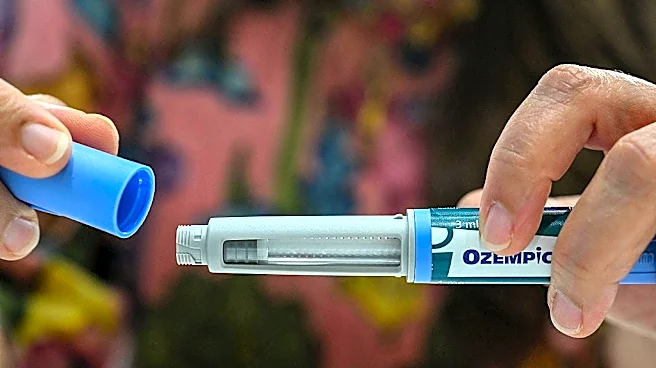
A new study from Washington University School of Medicine in St. Louis indicates that stopping GLP-1 medications, such as Ozempic and similar drugs, significantly elevates the risk of heart attacks and strokes. The research, which followed over 333,000
U.S. veterans with type 2 diabetes for three years, found that the cardiovascular benefits of these drugs are not permanent and diminish rapidly once treatment ceases. Discontinuation leads to a loss of cardioprotective effects, resulting in higher blood pressure, elevated cholesterol levels, and increased systemic inflammation. These factors collectively contribute to a greater cardiovascular risk. The study highlights that prolonged discontinuation is associated with progressively worse outcomes compared to continuous treatment. While the viral figure of a 22% increased risk has circulated, it does not imply that stopping Ozempic raises everyone's heart attack risk by 22% above their pre-treatment risk. The most effective approach to reducing stroke occurrence remains primary prevention, which includes lifestyle modifications and managing risk factors like obesity and high blood sugar.
Why It's Important?
This finding is crucial for public health and medical practice in the U.S., particularly given the widespread use of GLP-1 medications for type 2 diabetes and weight management. The study underscores that the cardiovascular benefits of these drugs are contingent on continuous use, challenging the perception that their positive effects might be sustained after cessation. For patients, this means that discontinuing treatment, whether due to cost, side effects, or other reasons, could expose them to a rapid return of cardiovascular risks that the medication was mitigating. Healthcare providers will need to emphasize the importance of adherence and discuss the potential consequences of stopping treatment with their patients. The implications extend to insurance providers and policymakers, who may need to consider long-term coverage strategies to ensure continuous access for patients who benefit from these drugs, thereby potentially reducing future healthcare costs associated with cardiovascular events.
What's Next?
The findings suggest a need for enhanced patient education regarding the long-term commitment required for GLP-1 therapies to maintain cardiovascular benefits. Healthcare providers may implement more rigorous counseling protocols to inform patients about the risks associated with discontinuing these medications. Further research is likely to focus on understanding the mechanisms behind the rapid loss of cardioprotection upon cessation and exploring strategies to mitigate these risks. This could include developing new formulations that offer more sustained benefits or identifying patient subgroups who might be more vulnerable to adverse outcomes after stopping treatment. Additionally, the study's results may influence discussions around insurance coverage and affordability, potentially leading to policies that support continuous access to GLP-1 drugs for patients who require them for cardiovascular risk reduction.
Beyond the Headlines
The study's revelations about the impermanence of GLP-1 drugs' cardiovascular benefits highlight a broader challenge in chronic disease management: the balance between immediate therapeutic gains and long-term adherence. This situation could lead to ethical dilemmas for patients facing financial constraints or experiencing side effects, as they weigh the immediate discomfort or cost against the long-term health risks of discontinuation. The findings also underscore the complex interplay between medication, lifestyle, and underlying health conditions, suggesting that a holistic approach to patient care is essential. Furthermore, it raises questions about the design of clinical trials and post-market surveillance, emphasizing the need for studies that specifically track outcomes after treatment cessation to provide a more complete picture of a drug's real-world impact. The 'metabolic whiplash' effect observed could also prompt a re-evaluation of how GLP-1 drugs are positioned in treatment guidelines, potentially shifting the focus towards continuous, rather than intermittent, therapy.